Back pain that keeps returning, limits walking or sleep, or fails to improve with a sensible self-care plan deserves more than repeated short-term treatment. You will learn which symptoms need urgent assessment, how clinicians connect examination findings with imaging, and when surgery offers a clearer benefit than continued non-operative care.
Key takeaways
- Seek assessment for pain lasting 12 weeks or causing weakness, numbness, or bladder changes.
- Persistent pain alone does not prove that spine surgery is needed.
- Compare imaging findings with symptoms, examination results, and functional limitations.
- Ask about expected benefit, risks, recovery time, and non-operative alternatives before consenting.
When does persistent back pain need medical assessment?
A practical persistent back pain definition is pain that continues for 12 weeks or longer, keeps returning, or restricts sleep, walking, work or daily activities despite sensible self-care. Chronic low-back pain is often non-specific: no single painful structure can be confirmed, and persistent pain alone does not prove that surgery is needed.
Seek urgent medical assessment if you develop:
- New bladder or bowel control loss, difficulty passing urine, numbness around the genitals or anus, or weakness that is worsening in both legs; these symptoms can indicate cauda equina syndrome.
- Severe back pain after a major fall, road crash or other trauma.
- Fever, chills or a recent serious infection alongside back pain, particularly with immune suppression or intravenous drug use.
- Unexplained weight loss, night pain that is increasing, or a personal history of cancer.
Common causes include muscle strain, degenerative disc disease, a herniated disc compressing a nerve, lumbar spinal stenosis, spondylolisthesis, vertebral fracture and inflammatory disease such as ankylosing spondylitis. A clinician will ask about duration, triggers, numbness, tingling and radiating leg pain, then check walking, reflexes, sensation and leg strength.
Imaging is reserved for cases where suspected serious disease or a treatable nerve problem would change management.
How are persistent back problems assessed before surgery is discussed?
Surgery is discussed only after a history and neurological examination connect your symptoms to a treatable spinal problem. The clinician asks when pain began, what worsens it, how far you can walk, whether you have radiating leg pain, and whether numbness and tingling or leg weakness is progressing.
The neurological examination checks walking, balance, reflexes, sensation and muscle strength. Heel and toe walking can reveal weakness that ordinary movement hides. The findings help distinguish nerve compression from non-specific back pain, where no single painful structure can be identified reliably.
Routine imaging is not useful for uncomplicated low-back pain when the result will not change treatment. Imaging becomes important when serious disease, a fracture, instability or a surgically treatable nerve problem is suspected.
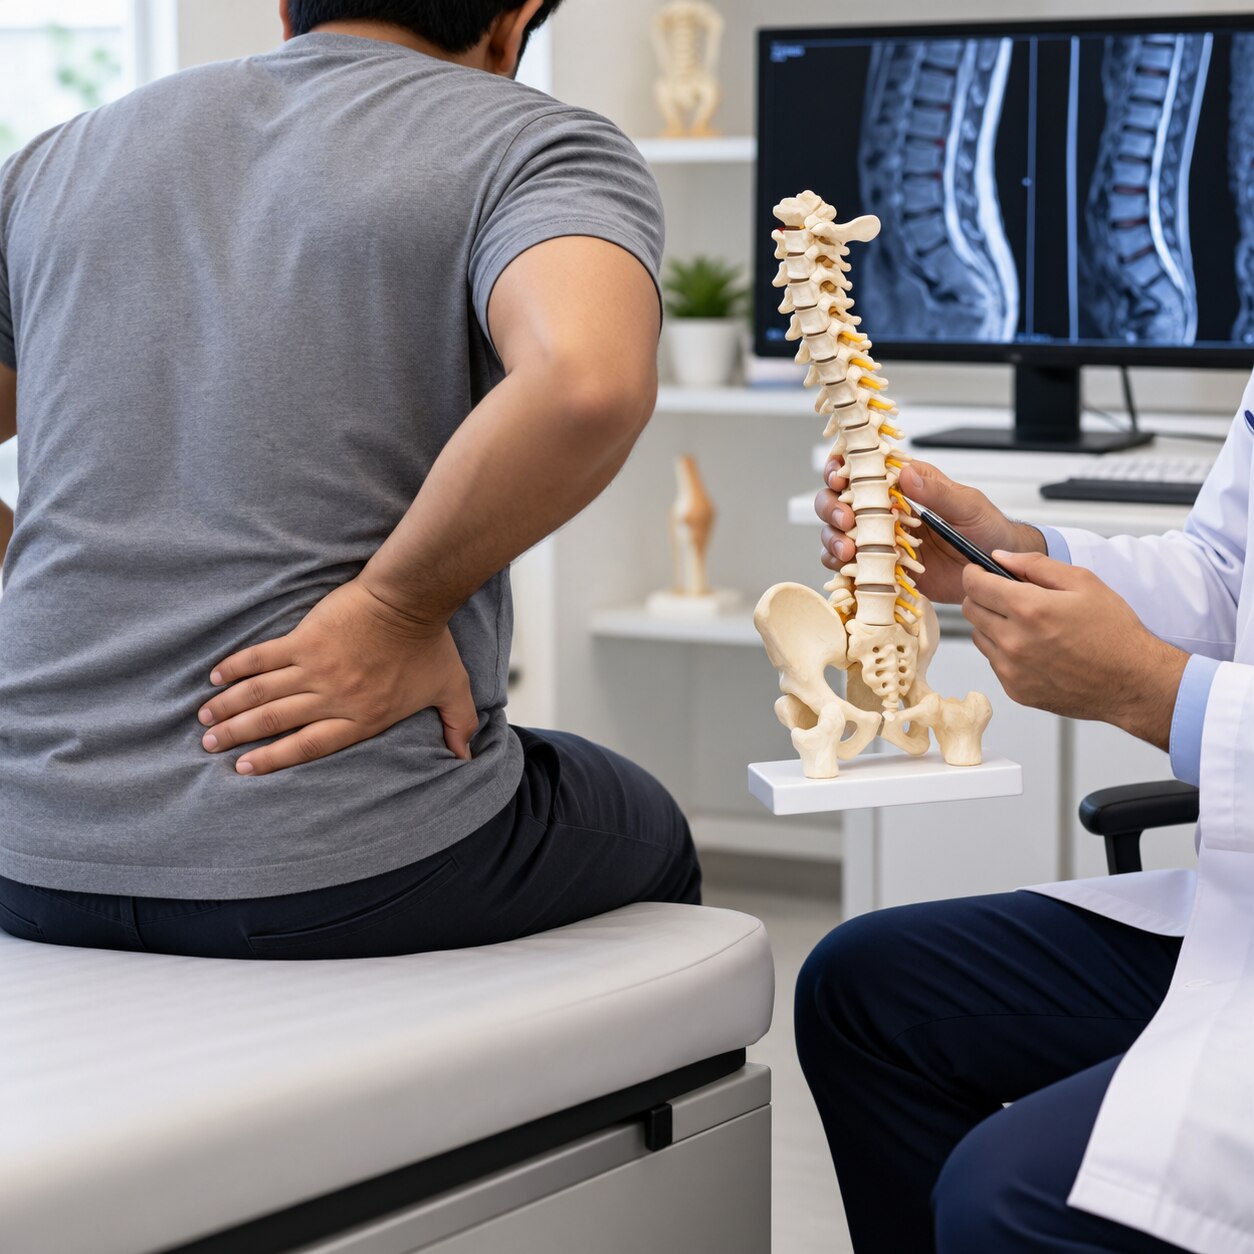
MRI shows discs, nerves, the spinal cord, infection, tumours and the soft-tissue narrowing seen in spinal stenosis. CT shows bone detail, including fractures, bony narrowing and fusion-planning anatomy. Spinal X-rays show alignment, vertebral height, curvature and slipping between vertebrae, especially on standing views. An abnormal scan matters only when it matches your symptoms and examination.
A genuine trial of non-surgical care includes:
1. Follow the agreed plan for an appropriate period, including activity modification, physiotherapy and prescribed medicines.
2. Record walking distance, sleep, work ability, radiating pain and neurological changes.
3. Reassess if function remains limited despite adherence, or if weakness, bladder or bowel symptoms develop.
When can the likely benefit of spine surgery outweigh continued non-operative care?
Surgery has its clearest value when a specific lesion explains a disabling symptom or neurological loss and an operation addresses that lesion. For lumbar spinal stenosis, spinal decompression relieves pressure on nerves causing leg pain, numbness or limited walking; it is less reliable for isolated, nonspecific low-back pain.
The procedure considered depends on the problem:
- A herniated disc with nerve compression can lead to discectomy when sciatica, examination findings and MRI point to the same nerve problem, and symptoms remain disabling despite non-operative care.
- Spinal instability from spondylolisthesis can require fusion with fixation when movement causes symptoms or threatens alignment.
- A vertebral fracture, deformity or failed previous operation can require reconstruction, sometimes combined with fixation, when stability or nerve protection cannot be restored more simply.
Pain intensity alone does not establish a surgical indication. An abnormal MRI does not do so either: disc bulges and age-related changes occur in people without symptoms. Surgery becomes more reasonable when progressive weakness, significant neurological impairment, or unacceptable leg pain and disability persists despite an appropriate treatment trial.
The decision should compare expected relief, surgical risks and recovery with the likely course of continued non-operative care; some disc-related sciatica improves without surgery, although an operation can provide faster relief.
What should you weigh before consenting to spine surgery?
A sound decision compares the expected gain from surgery with both its risks and the likely course without it. Waiting can allow progressive weakness or disability to persist, but pain duration alone does not make surgery urgent.
In selected disc-related sciatica, surgery can relieve leg pain faster; it may not remove persistent back pain, and the advantage can narrow as non-operative recovery occurs.
1. Ask what the operation is designed to improve. Decompression or discectomy mainly targets nerve-related leg pain, numbness or weakness; fusion also carries hardware, non-union and adjacent-segment problems. An abnormal MRI does not guarantee relief.
2. Ask about procedure-specific spine surgery risks, including infection, blood clots, nerve injury, dural tear and cerebrospinal-fluid leak. Request the surgeon’s estimated risk for your operation and health conditions.
3. Plan for the practical burden: hospital admission, help at home, dressing and wound checks, restrictions on bending and lifting, when you may drive, time away from work, physiotherapy and follow-up appointments.
4. Ask how long recovery should take and what happens if symptoms remain. Reoperation may be needed for recurrent compression, failed fusion, hardware problems or new disease; a second operation is not guaranteed to restore function.
Get written instructions before discharge, including permitted lifting weight, warning signs and the emergency contact number.
How should you prepare for a consultation or second opinion?
Take a one-page timeline to the appointment: when pain began, where it travels, what worsens it, weakness or numbness, treatments tried, and how walking, sleep, work or school have changed. Bring MRI, CT and X-ray images, reports, medication names, physiotherapy notes and operative records.
1. Write your spine surgery consultation questions in advance. Ask which diagnosis matches your symptoms, what surgery targets, what happens if you wait, and how success will be measured.
2. State your age and health conditions. Children with back pain need assessment that considers growth, activity and age-specific causes; older adults may have several spinal changes that do not explain the pain.
3. If you had previous surgery, bring the exact procedure and date. Persistent symptoms after an operation may be called failed back surgery syndrome, but that label does not identify the pain source; request a fresh review of the images and examination.
4. Ask what evidence links the proposed operation to your symptoms when pain is widespread or non-specific.
5. Define your expected result—walking farther, less leg pain, better sleep or complete pain relief. A second opinion is most valuable when the diagnosis, benefit, risks or goal remains unclear.
What can a spine-care pathway look like at Dhanvantari Hospital?
A spine evaluation for Panvel patients at Dhanvantari Hospital can start with symptom history, walking assessment, strength, reflexes and sensation testing. The clinician then decides whether imaging will change treatment rather than ordering an MRI automatically.
- Urgent trauma referral takes priority after major injury, or with new bladder or bowel loss, saddle numbness, progressive weakness, fever or suspected infection.
- Imaging review matches MRI, CT or X-ray findings with the examination; a disc bulge without matching nerve symptoms does not establish a surgical problem.
- Conservative spine treatment may include activity guidance, structured exercise, pain management and education, with progress judged by function rather than time alone.
- Surgical discussion follows only when a confirmed compressive problem causes unacceptable pain, disability or neurological decline despite suitable non-operative care.
- Orthopaedic rehabilitation supports recovery after conservative treatment or surgery, including graded movement, strength work and return-to-work planning.
This sequence keeps surgery as one option, not the automatic endpoint. It also leaves room to reassess the diagnosis when symptoms, examination and imaging do not agree.
Related services
Spine Surgery Treatment At Dhanvantari Hospital, Dr. Anand Upadhye and Dr. Sushant Upadhye provides advanced and specialized Spine Surgery Treatment for patients suffering... View service → |
Back Pain And Joint Pain Clinic Back Pain And Joint Pain Clinic At Dhanvantari Hospital, Dr. Anand Upadhye and Dr. Sushant Upadhye offers specialized diagnosis and treatment for back pain, joint pain, neck pain,... View service → |
Frequently asked questions
When does persistent back pain need medical assessment?
Seek assessment when pain lasts 12 weeks, repeatedly returns, disrupts sleep or daily activities, or continues despite sensible self-care. Obtain urgent care for new leg weakness, numbness around the groin, or loss of bladder or bowel control.
How are persistent back problems assessed before surgery is discussed?
Assessment combines your history, physical and neurological examination, review of function, and imaging such as X-rays or MRI when indicated. The findings must match your symptoms before surgery is considered.
When can spine surgery be considered for persistent back pain?
Surgery may be considered when a specific spinal problem explains your symptoms, non-operative treatment has not restored function, and the expected benefit outweighs the risks and recovery demands.
What should you weigh before consenting to spine surgery?
Discuss the exact procedure, expected improvement, risks, complications, recovery timeline, restrictions, rehabilitation, alternatives, and what happens if symptoms persist.
How should you prepare for a spine consultation or second opinion?
Bring a symptom timeline, medication list, treatment records, imaging reports and discs, relevant medical history, and written questions about diagnosis, options, outcomes, and recovery.